Diagnosing Diseases Using kNN
An Application of kNN to Diagnose Diabetes
Elena Boiko, Jacqueline Razo (Advisor: Dr. Cohen)
2026-11-01
Introduction
In healthcare, kNN has shown promise in predicting chronic diseases like diabetes (Suriya and Muthu 2023) and hypertension (Khateeb and Usman 2017).
In this project, we focus on how kNN can be applied and optimized to predict diabetes, a critical and growing public health issue.
Why This Matters
- Diabetes affects millions worldwide. Early detection can improve outcomes.
- Machine learning, especially interpretable models like kNN, can support diagnosis.
- Our project explores:
- How different k values, distance metrics, and preprocessing techniques affect kNN’s performance.
- Whether kNN is competitive with other models for this task.
Why We Chose kNN for This Project
Well-suited for medical datasets with small to medium size
Easy to interpret — great for health professionals
Flexible with minimal assumptions
Can impute missing data and detect patterns
Our Approach
- Clean and preprocess real-world survey data.
- Train kNN models with various configurations.
- Evaluate performance and compare with tree-based models.
Method: kNN Overview
k-Nearest Neighbors (kNN) is a non-parametric, instance-based learning algorithm
It is a lazy learner — no explicit training phase is required
Instead, it classifies new data based on similarity to existing labeled points (Zhang 2016)
Classification Process:
1. Distance Calculation:
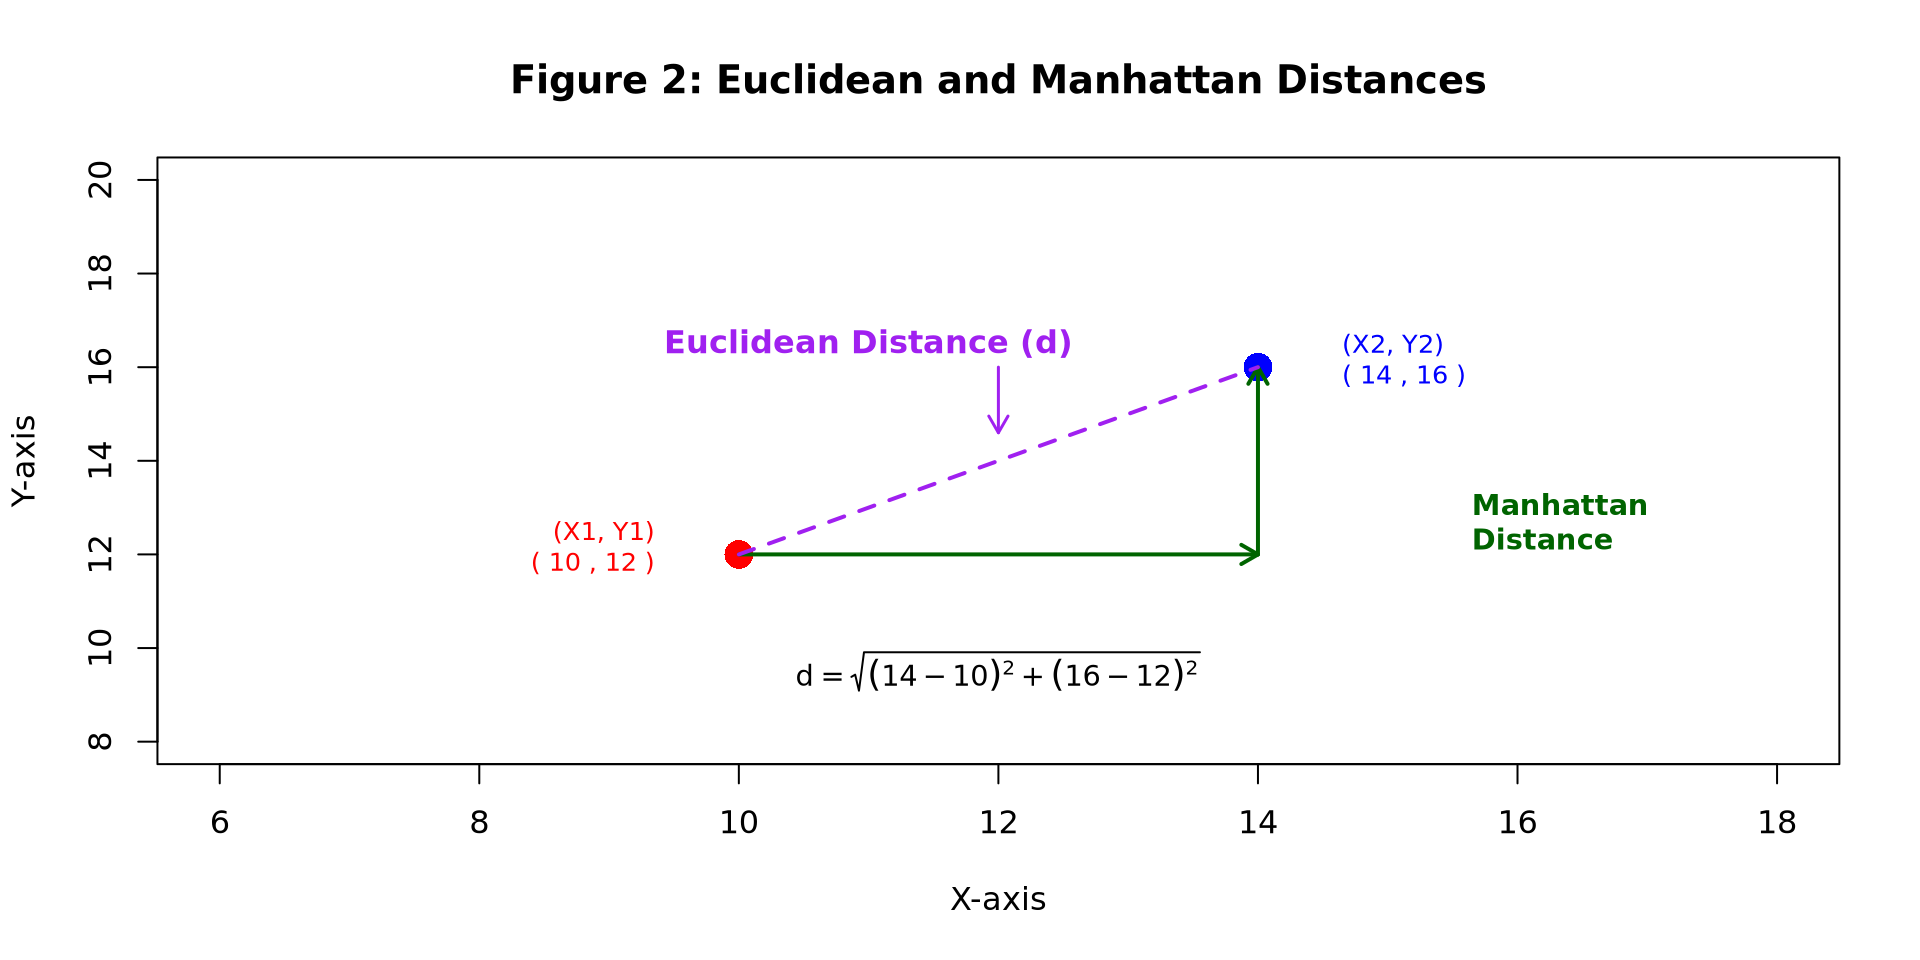
Measures similarity using metrics like Euclidean or Manhattan distance
2. Neighbor Selection:
Hyperparameter k defines how many nearby points to consider
3. Majority Voting:
The most frequent class among the k nearest neighbors determines the prediction
Distance Calculation:
kNN identifies the nearest neighbors by calculating distances between points.
Euclidean distance: (Theerthagiri et al. 2022) \[ d = \sqrt{(X_2 - X_1)^2 + (Y_2 - Y_1)^2} \]
Manhattan distance: (Aggarwal et al. 2015) \[ d = |X_2 - X_1| + |Y_2 - Y_1| \]
Classification Process
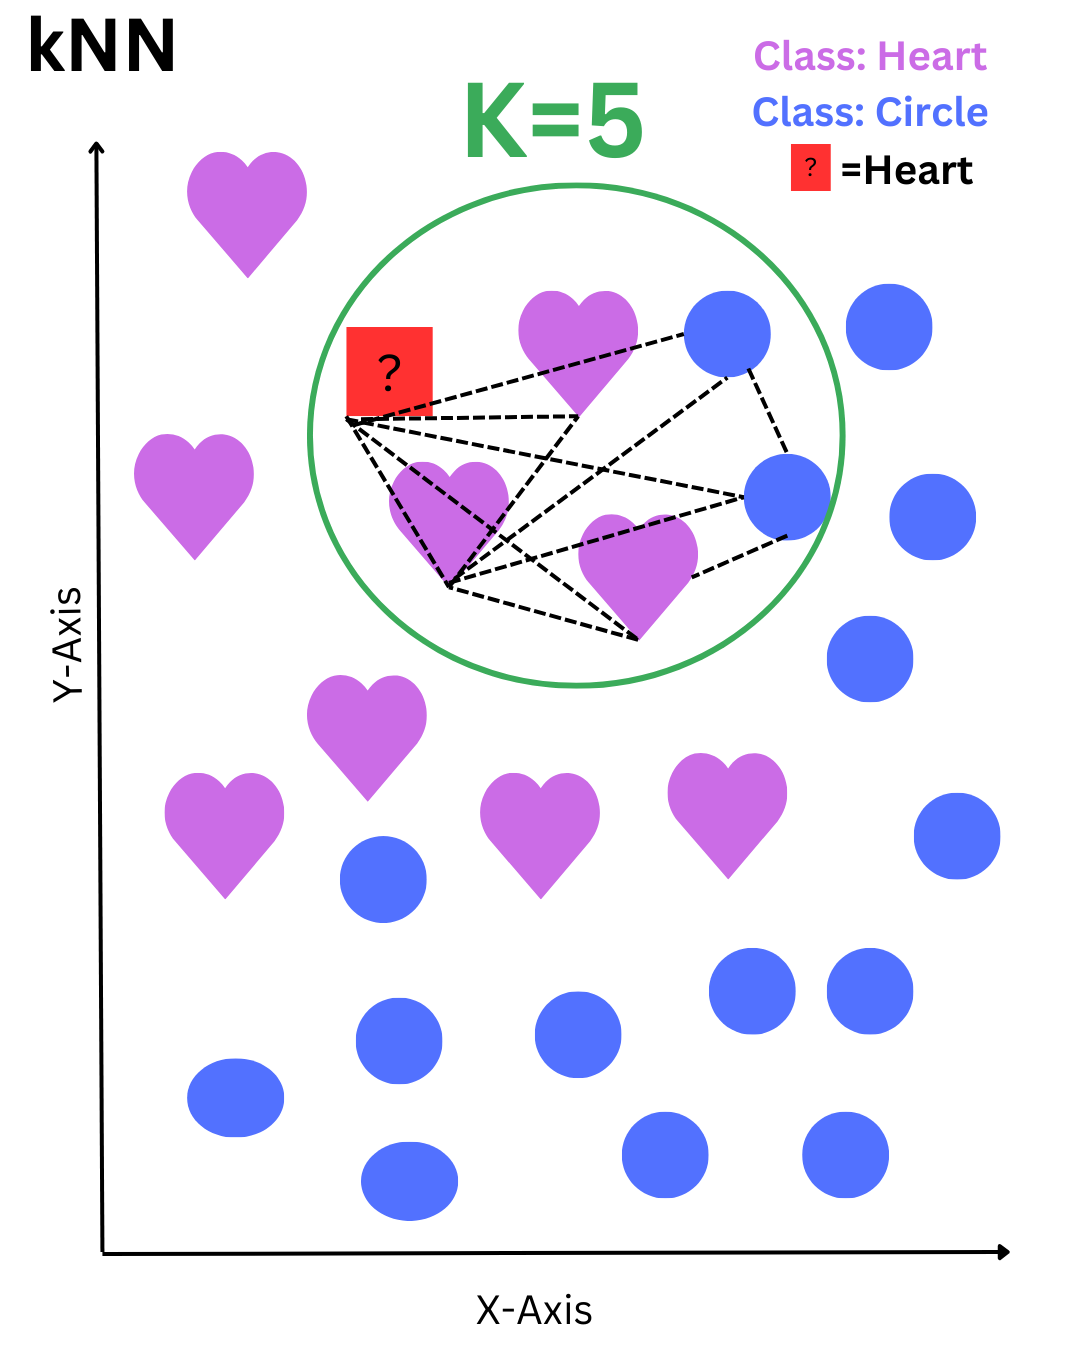
The red square represents a data point to be classified. The algorithm selects the 5 nearest neighbors within the green circle—3 hearts and 2 circles. Based on the majority vote, the red square is classified as a heart.
Strengths and Weaknesses of kNN
Strengths
- Simple, intuitive, and non-parametric — no assumptions about data distribution
- No training phase — the algorithm learns during prediction
- Performs well on small to medium datasets, especially when features are well-scaled
- Easy to understand and implement — ideal for baseline models or educational use
Weaknesses of kNN
- Slow prediction time on large datasets due to distance calculations (Deng et al. 2016)
- Sensitive to feature scaling and distance metric choice (Uddin et al. 2022)
- Choosing the right ‘k’ is critical — too low or high can reduce performance
- Affected by irrelevant or correlated features, which may distort neighbor similarity
Analysis and Results
Data Source and Collection
Data Source: CDC Diabetes Health Indicators
Collected via the CDC’s Behavioral Risk Factor Surveillance System (BRFSS)
Dataset contains 253,680 survey responses
Covers 21 features: demographics, lifestyle, healthcare, and health history
Target: Diabetes_binary
(0 = No diabetes, 1 = Diabetes/Prediabetes)
Data Challenges
Data Quality
No missing values
24,206 duplicate rows detected
Outliers & Scaling Sensitivity
BMI, MentHlth, PhysHlth had extreme values
kNN is highly sensitive to scale
Feature Relationships
No strong multicollinearity (max r = 0.52)
All features retained for now
Early Insight
Higher BMI in diabetic cases, but overlapping range
Used as a predictor along with other features
Class Distribution:
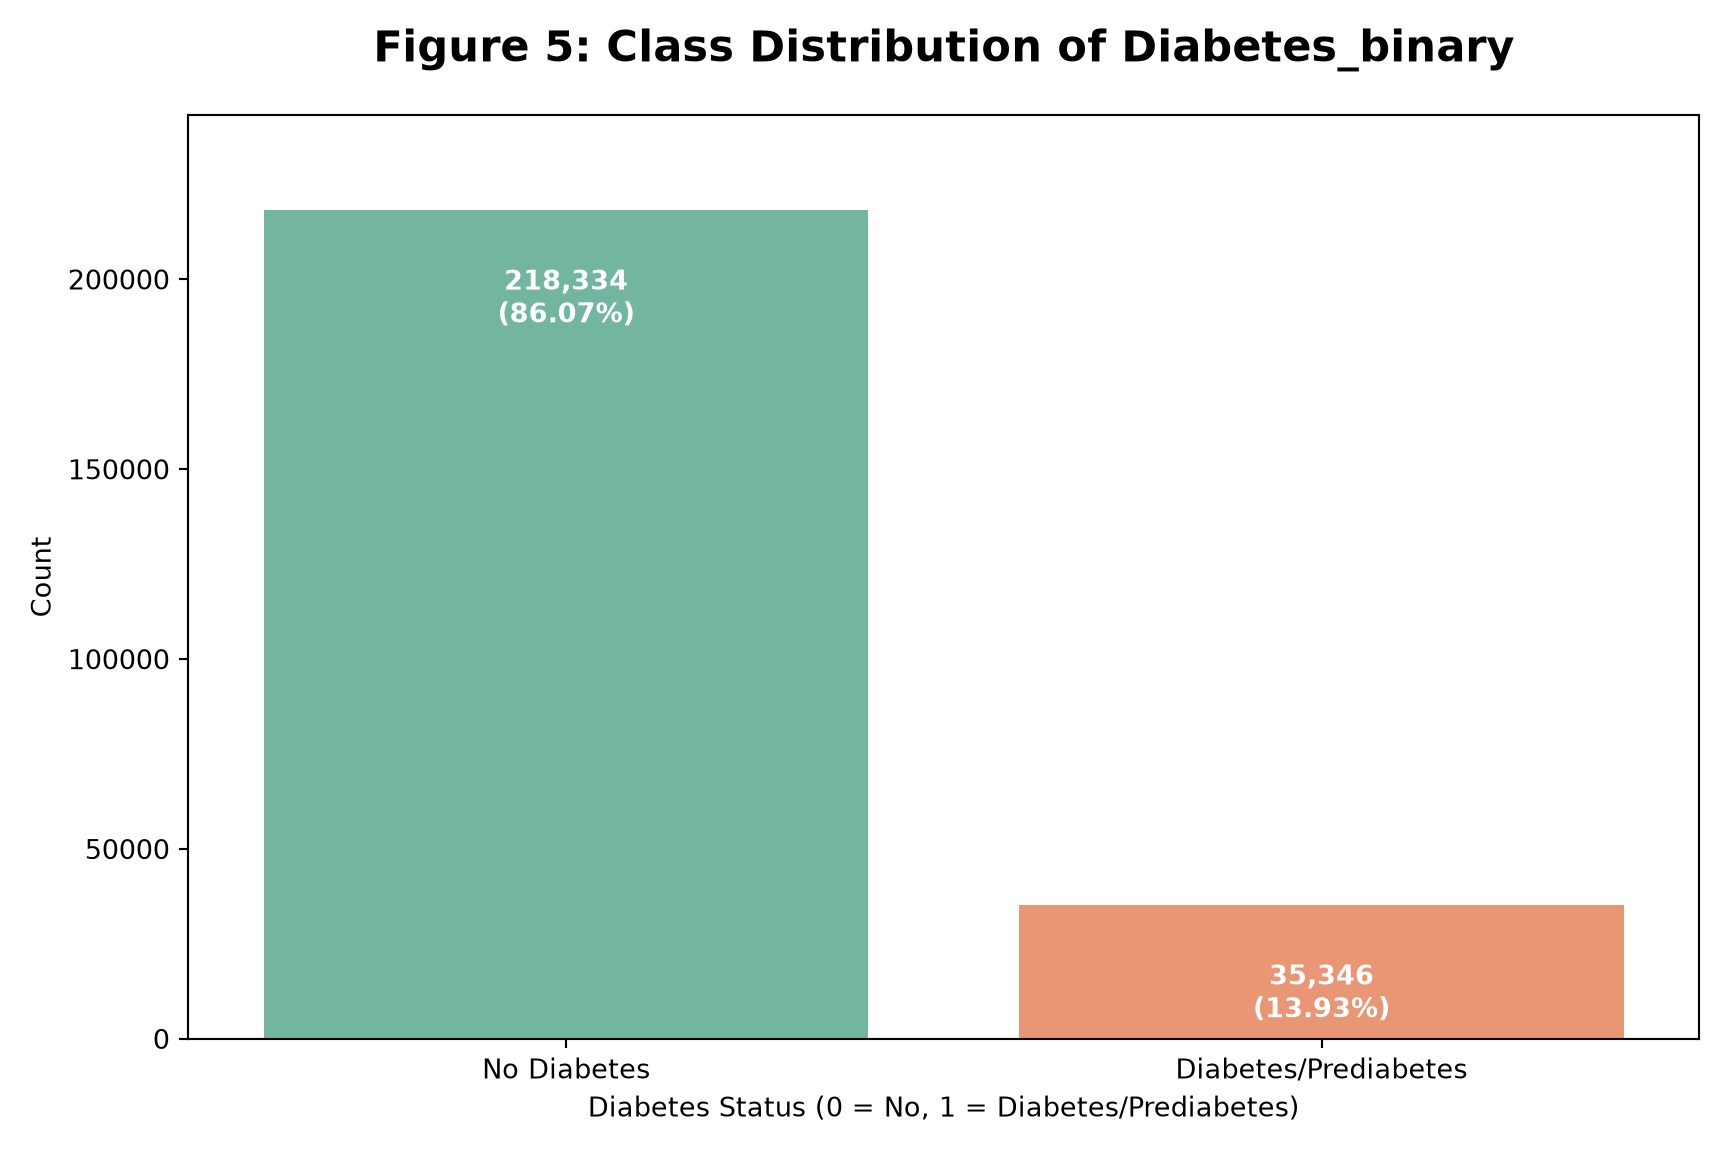
Diabetes Class Imbalance
Key Points
Significant class imbalance observed
Majority class: No Diabetes (0) – 86.07%
Minority class: Diabetes (1) – 13.93%
Impact on Modeling
Imbalance can bias predictions
Models may underpredict diabetes cases
Preparing the Data
Removed 24,206 duplicate rows
Diabetic class increased from 13.9% → 15.3%Kept ordinal features as numeric
Age, Education, Income, and GenHlth retained due to natural orderingScaled Features with Outliers
Features scaled with StandardScaler or RobustScaler (fitted on training data)Handled class imbalance
Applied SMOTE to generate synthetic diabetic samples
➡️ Final dataset: clean and scaled; SMOTE applied to training data only
kNN Model Setup
- Explored different k values: 5, 10, 15
- Compared distance metrics: Euclidean vs. Manhattan
- Evaluated weighting methods: uniform vs. distance
- Tested multiple scaling techniques
- Included variations with SMOTE and Feature Selection
| Model | k | Distance | Weights | Scaler | SMOTE |
|---|---|---|---|---|---|
| kNN 1 | 5 | Euclidean (p=2) | Uniform | StandardScaler | No |
| kNN 2 | 15 | Manhattan (p=1) | Distance | RobustScaler | No |
| kNN 3 | 10 | Euclidean (p=2) | Uniform | StandardScaler | Yes |
| kNN 4 | 15 | Euclidean (p=2) | Distance | StandardScaler | Yes (Feature Selection) |
Performance of kNN Variants
Table 4: Performance Comparison of kNN Models
| Model | k | Distance | Weights | Scaler | SMOTE | Accuracy | ROC_AUC | PR_AUC | Precision_1 | Recall_1 | F1_1 |
|---|---|---|---|---|---|---|---|---|---|---|---|
| kNN 1 | 5 | Euclidean (p=2) | Uniform | StandardScaler | No | 0.832 | 0.705 | 0.281 | 0.406 | 0.206 | 0.274 |
| kNN 2 | 15 | Manhattan (p=1) | Distance | RobustScaler | No | 0.841 | 0.752 | 0.334 | 0.446 | 0.155 | 0.230 |
| kNN 3 | 10 | Euclidean (p=2) | Uniform | StandardScaler | Yes | 0.691 | 0.733 | 0.286 | 0.278 | 0.641 | 0.388 |
| kNN 4 | 15 | Euclidean (p=2) | Distance | StandardScaler | Yes (FS) | 0.731 | 0.722 | 0.300 | 0.303 | 0.579 | 0.397 |
Best ROC-AUC among kNN: kNN 2 (0.752)
RobustScaler, Manhattan distance, distance weightingSMOTE raised recall from ~0.2 to 0.58–0.64
at the cost of lower precisionFeature selection (kNN 4): 12 features instead of 21, mixed results vs. kNN 3
Comparing kNN with Tree Models
Table 5: kNN 4 vs. Tree-Based Models
| Model | SMOTE | Accuracy | ROC_AUC | PR_AUC | Precision_1 | Recall_1 | F1_1 |
|---|---|---|---|---|---|---|---|
| KNN 4 | Yes | 0.731 | 0.722 | 0.300 | 0.303 | 0.579 | 0.397 |
| Decision Tree | Yes | 0.671 | 0.756 | 0.317 | 0.281 | 0.740 | 0.407 |
| Decision Tree | No | 0.849 | 0.794 | 0.388 | 0.517 | 0.154 | 0.237 |
| Random Forest | No | 0.854 | 0.813 | 0.432 | 0.599 | 0.134 | 0.219 |
- Random Forest had the best ROC-AUC (0.813) and PR-AUC (0.432)
- Decision Tree with SMOTE had the highest recall (0.740) and F1 (0.407)
- Random Forest had highest accuracy, but poor recall (0.13) shows it struggled to detect diabetic cases
Tree-based models offer interpretability, but may need tuning or resampling for minority detection
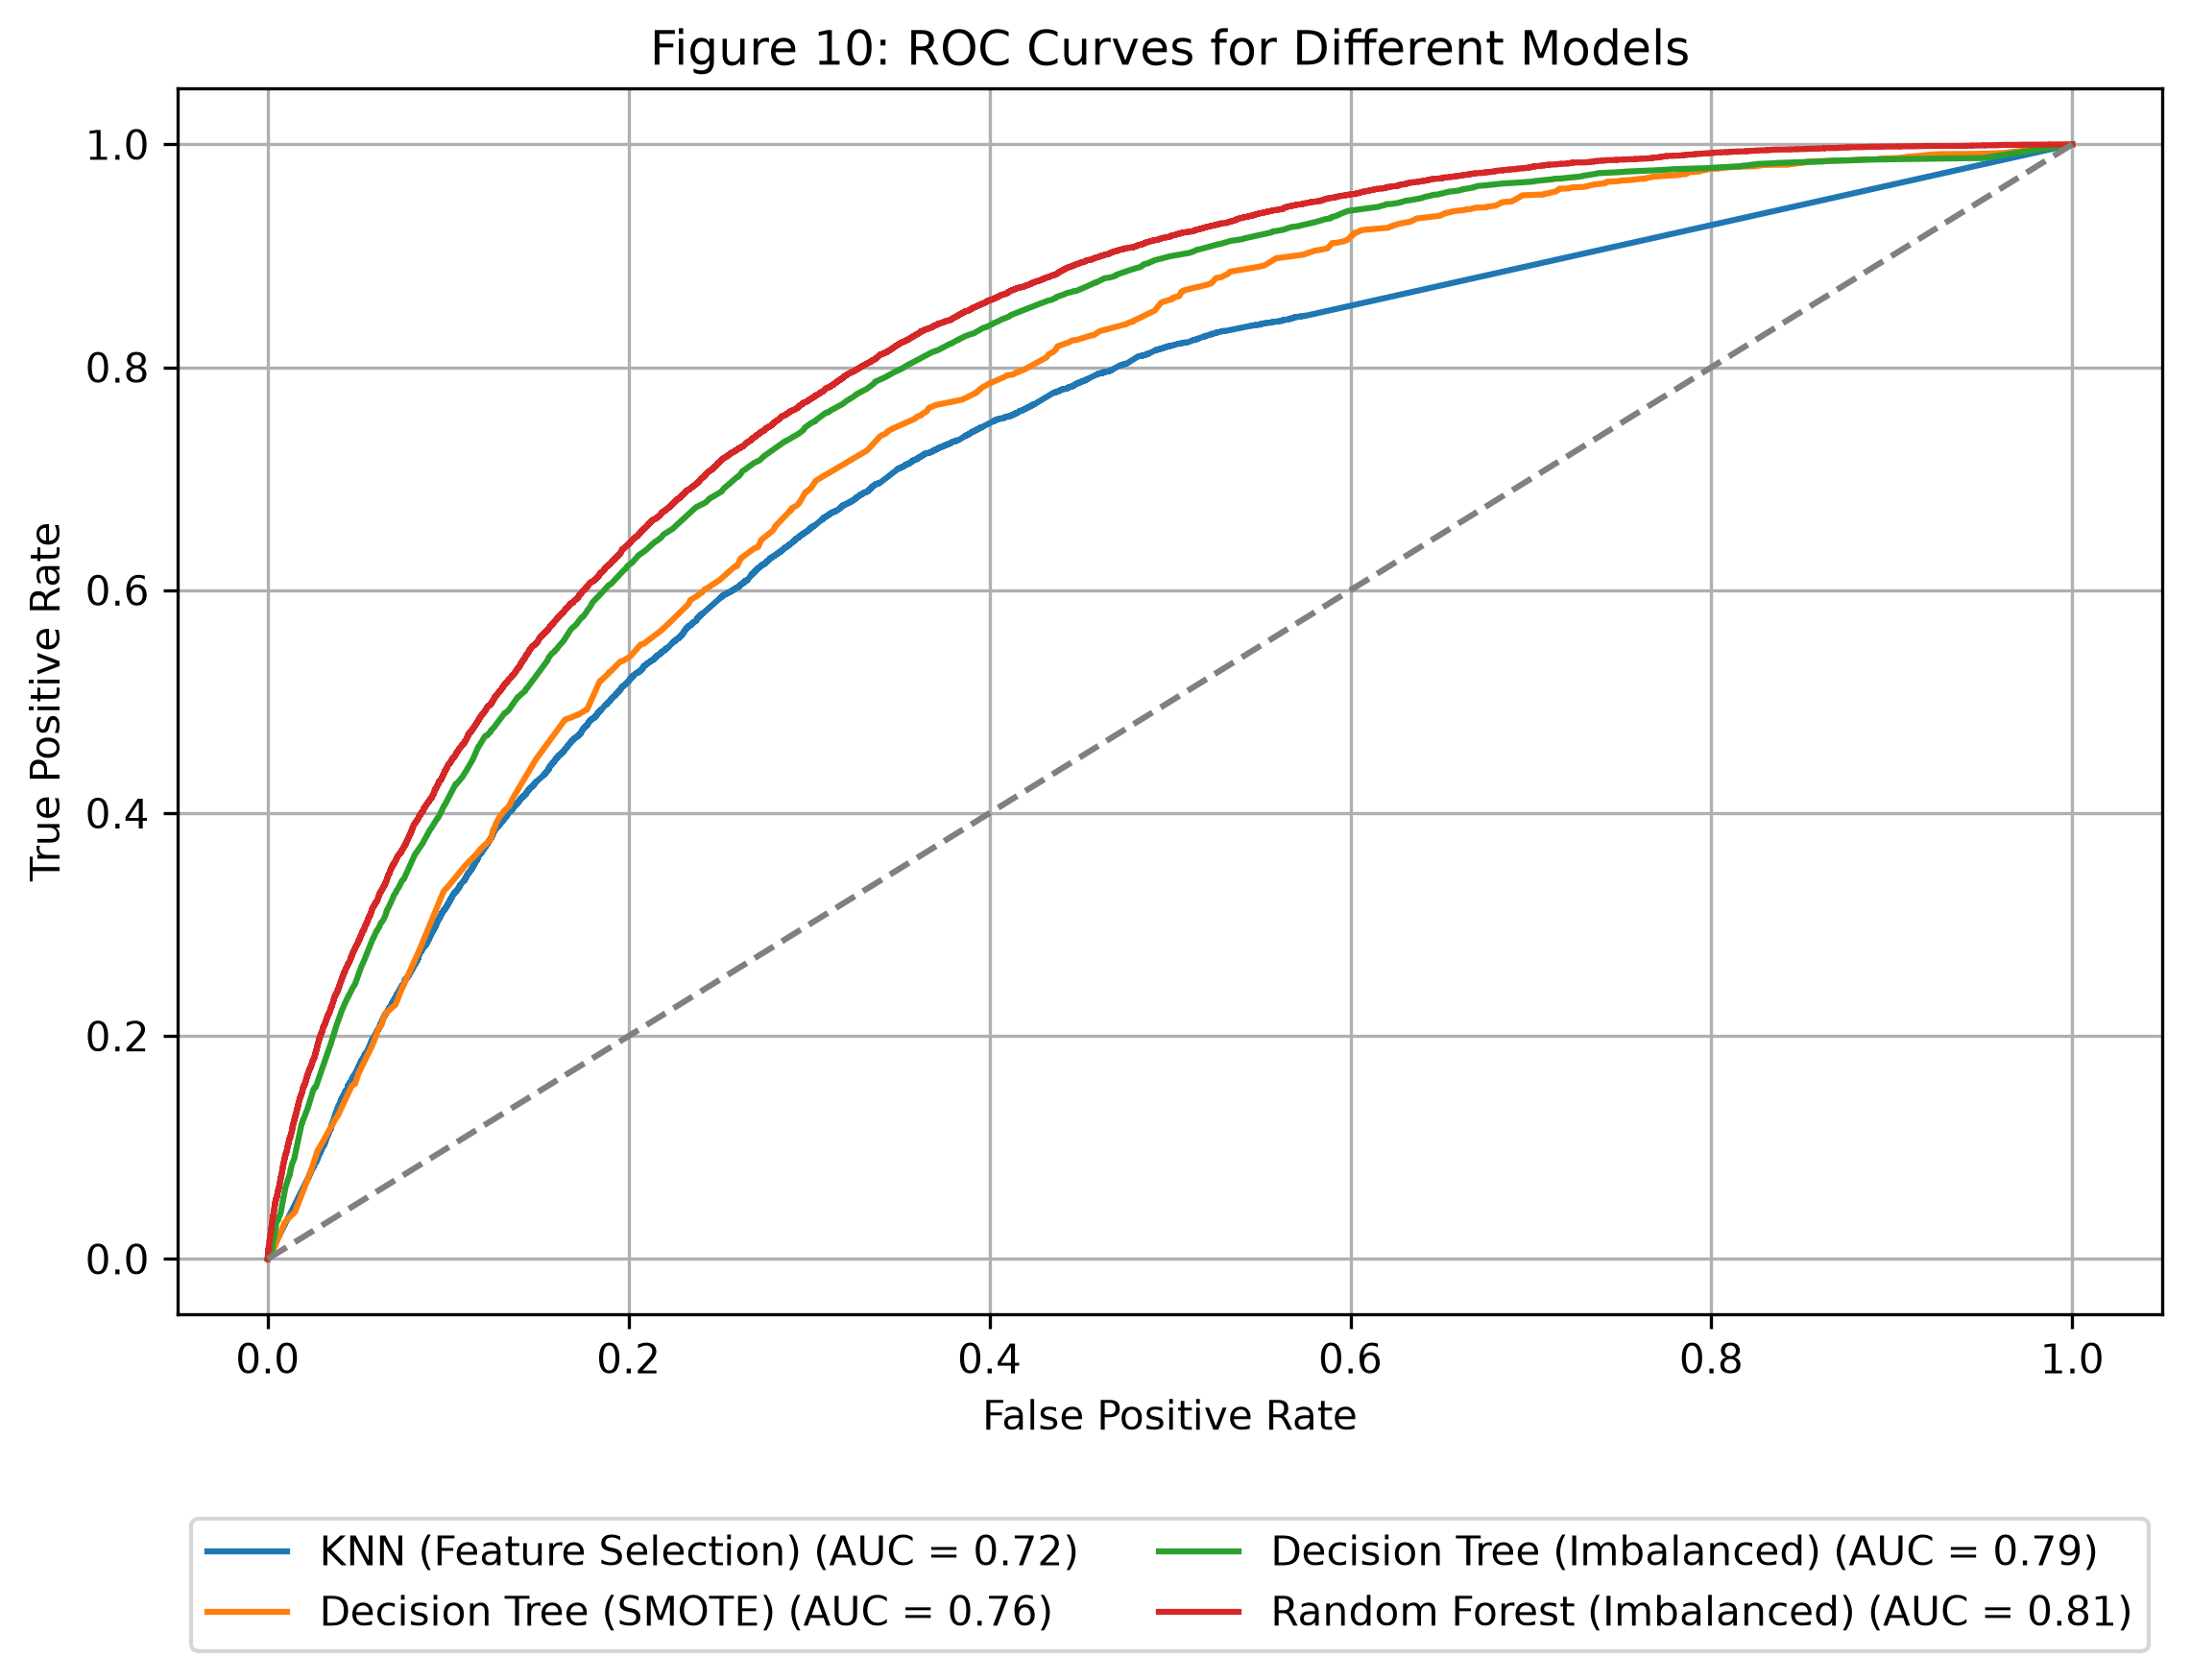
ROC_AUC curves comparison
ROC curves of kNN 4 and the tree-based models on the same test set.
Random Forest has the highest AUC (0.81), kNN 4 reaches 0.72.
ROC Curve
Conclusion
Preprocessing changes kNN’s behavior: configurations with SMOTE had ~3× higher recall for diabetic cases (~0.6 vs. ~0.2); RobustScaler, Manhattan distance, k = 15 and distance weighting (kNN 2) improved ROC-AUC (0.70 → 0.75).
On this large dataset, tree-based models achieved higher ROC-AUC: Random Forest had the best ROC-AUC (0.813), Decision Tree with SMOTE the highest recall (0.740).
No single best model: the choice of model and metric should follow the goal of the analysis.
Accuracy alone is misleading for imbalanced medical data.
Revision 2026: the original evaluation of kNN 4 (AUC 0.88) contained data leakage; all models were re-evaluated on one untouched test set.
References
Aggarwal, Charu C et al. 2015. Data Mining: The Textbook. Vol. 1. Springer.
Deng, Zhenyun, Xiaoshu Zhu, Debo Cheng, Ming Zong, and Shichao Zhang. 2016. “Efficient kNN Classification Algorithm for Big Data.” Neurocomputing 195: 143–48.
Khateeb, Nida, and Muhammad Usman. 2017. “Efficient Heart Disease Prediction System Using k-Nearest Neighbor Classification Technique.” Proceedings of the International Conference on Big Data and Internet of Thing, 21–26.
Suriya, S, and J Joanish Muthu. 2023. “Type 2 Diabetes Prediction Using k-Nearest Neighbor Algorithm.” Journal of Trends in Computer Science and Smart Technology 5 (2): 190–205.
Theerthagiri, Prasannavenkatesan, A Usha Ruby, and J Vidya. 2022. “Diagnosis and Classification of the Diabetes Using Machine Learning Algorithms.” SN Computer Science 4 (1): 72.
Uddin, Shahadat, Ibtisham Haque, Haohui Lu, Mohammad Ali Moni, and Ergun Gide. 2022. “Comparative Performance Analysis of k-Nearest Neighbour (KNN) Algorithm and Its Different Variants for Disease Prediction.” Scientific Reports 12 (1): 6256.
Zhang, Zhongheng. 2016. “Introduction to Machine Learning: K-Nearest Neighbors.” Annals of Translational Medicine 4 (11).